99213 CPT code: low-complexity MDM or 20+ minutes
CPT 99213 is the third of five established-patient office or outpatient visit codes, 99211 through 99215. In our words: an established patient visit of low complexity. Since January 1, 2023, Medicare has let the practitioner pick the level of most E/M visit families either by MDM or by the physician's or non-physician practitioner's time, according to Medicare Claims Processing Manual chapter 12, section 30.6.1. For 99213 that means low MDM or at least 20 minutes, the threshold in the AAFP's table of E/M time and MDM levels. You need one path, not both.
Established patient: the 3-year test
99213 is for an established patient only. The CMS Evaluation and Management Services booklet (MLN006764, May 2026) defines an established patient as someone who received professional services from the physician, the non-physician practitioner (NPP) or another physician of the same specialty in the same group practice within the previous 3 years. A patient outside that window is new and takes 99202-99205. Chapter 12, section 30.6.7 narrows the professional service to an E/M or other face-to-face service: a test interpretation alone, such as reading an EKG, does not make the patient established. The test turns on the specialty and the group, so a same-specialty partner's visit two years ago makes the patient established for every physician of that specialty in your group.
Billing 99213 by time: the full 20 minutes
Chapter 12 says that when time selects the level, the full time must be completed, and the general CPT midpoint rule for timed services does not apply. A 19-minute visit is therefore not 99213 by time: it is 99212 by time, unless the MDM supports 99213. At 30 minutes the visit reaches the 99214 threshold. History and exam must still be performed as the code requires, but they no longer change the level. The same section warns that documentation volume should not drive the level and that billing a higher level is not medically necessary when a lower one fits.
A nurse practitioner, clinical nurse specialist or physician assistant can bill 99213 to Medicare when it is within their state scope of practice (chapter 12, section 30.6.1). Medicare pays NPs and CNSs 80 percent of the lesser of the actual charge or 85 percent of the physician fee schedule amount (section 120).
| Requirement | What Medicare expects for 99213 | Source |
|---|---|---|
| Patient type | Established: an E/M or other face-to-face service from the same clinician or same-specialty group within 3 years | MLN006764; CPM ch. 12, 30.6.7 |
| Level by MDM | Low MDM under the CPT guidelines Medicare applies | CPM ch. 12, 30.6.1; AAFP |
| Level by time | At least 20 minutes of physician or NPP time on the date, no midpoint rounding | CPM ch. 12, 30.6.1; AAFP |
| History and exam | Performed as the code requires; does not set the level | CPM ch. 12, 30.6.1 |
| Documentation volume | Not the basis for the level; the record supports the level billed | CPM ch. 12, 30.6.1; MLN006764 |
| 2026 national Medicare amount (unadjusted) | $95.19 office (non-facility), $57.45 facility | CMS RVU26D via our PFS dataset |
E and M codes at a glance: 99202-99205 and 99211-99215
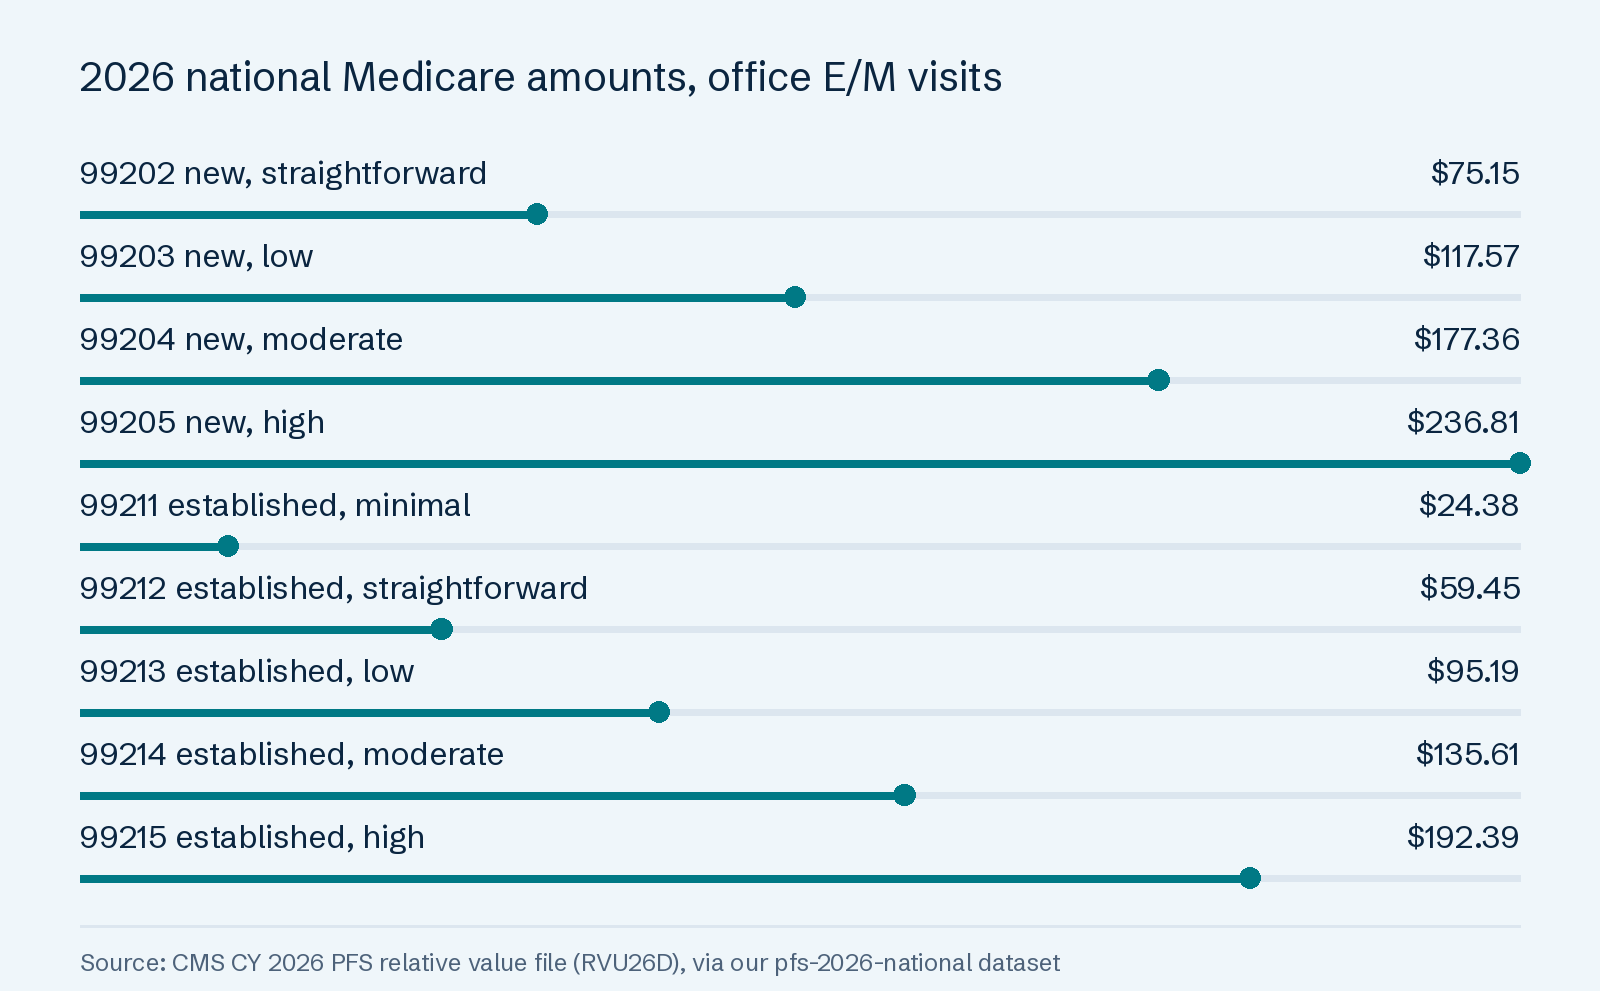
The office and outpatient E/M family has four new-patient codes and five established-patient codes. Each level above 99211 is met by an MDM level or a minimum total time on the date of the visit. The AAFP table states that neither total time nor MDM applies to 99211, the minimal established visit. The amounts below are 2026 national Medicare amounts (unadjusted) from the CMS calendar year 2026 relative value file (RVU26D), at the $33.4009 conversion factor for clinicians who are not qualifying APM participants. Actual payment varies by locality, setting and payer, and commercial plans pay their contracted rates.
Read the table across a row: the descriptions are our plain-English summaries, not the AMA's descriptor text. A wrong new-or-established flag moves real money. The same moderate-complexity visit is $177.36 as 99204 and $135.61 as 99214 in the office.
Visits that run past the top level
Medicare uses its own add-on, G2212, for prolonged office time; the CPT prolonged code 99417 carries status I (not valid for Medicare) in the 2026 file. MLN006764's table puts 99215 at 40-54 minutes and 99215 plus one unit of G2212 at 69-83 minutes; 99205 is 60-74 minutes and 99205 plus one G2212 is 89-103 minutes. G2212 is never reported for less than 15 additional minutes. Its 2026 national Medicare amount (unadjusted) is $34.07 non-facility.
| Code | Our short description | MDM level | Or total time (at least) | 2026 national Medicare amount (unadjusted), office / facility |
|---|---|---|---|---|
| 99202 | New patient visit, straightforward | Straightforward | 15 minutes | $75.15 / $41.08 |
| 99203 | New patient visit, low complexity | Low | 30 minutes | $117.57 / $71.48 |
| 99204 | New patient visit, moderate complexity | Moderate | 45 minutes | $177.36 / $116.90 |
| 99205 | New patient visit, high complexity | High | 60 minutes | $236.81 / $160.32 |
| 99211 | Established visit, minimal | Not applicable | Not applicable | $24.38 / $7.68 |
| 99212 | Established visit, straightforward | Straightforward | 10 minutes | $59.45 / $31.06 |
| 99213 | Established visit, low complexity | Low | 20 minutes | $95.19 / $57.45 |
| 99214 | Established visit, moderate complexity | Moderate | 30 minutes | $135.61 / $84.50 |
| 99215 | Established visit, high complexity | High | 40 minutes | $192.39 / $125.59 |
99212, 99214 and 99215: picking the level by MDM or total time
The level is the higher of what the MDM or the clinician's total time supports, and either path alone is enough. The line between 99213 and 99214 is one MDM level or 10 minutes, and each step up the established ladder adds money: at the 2026 national Medicare amount (unadjusted), office, 99214 pays $40.42 more than 99213 ($135.61 against $95.19), and 99215 pays $56.78 more than 99214.
MDM: two of three elements
MDM has three elements, as the American College of Surgeons' summary of the office E/M rules lists them: the number and complexity of problems addressed, the amount and complexity of data reviewed and analyzed, and the risk of complications from the management chosen. The MDM level is based on 2 of the 3 elements. Prescription drug management is one of the examples ACS lists at moderate risk, which is why a medication change for a chronic condition so often sits at 99214 when a second element also reaches moderate.
Time: count the clinician's day, not the face time
On the time path, total time is the practitioner's time on the date of the visit. 99212 needs 10 minutes, 99214 needs 30 and 99215 needs 40 (AAFP). Medicare adds the full-time rule, so 39 minutes is 99214, not 99215.
Work every established office visit in this order:
- Confirm the patient type. Any E/M or other face-to-face service from the clinician or a same-specialty colleague in the group within 3 years means established (MLN006764; chapter 12, section 30.6.7).
- Pick the path the note supports. MDM or total time; you do not need both.
- On MDM, test two of three. Problems, data and risk; two must reach the level you bill.
- On time, add the minutes. Check the note shows the total, and that it meets the full threshold.
- Check same-day services. A procedure or psychotherapy the same day changes the rules (sections below).
- Decide on G2211 for Medicare. It applies to ongoing focal-point care and is blocked on most modifier 25 visits.
| Level | MDM path | Time path (Medicare: full time) | Common reason it fails review |
|---|---|---|---|
| 99212 | Straightforward MDM | 10+ minutes | Billed where 99211-level work was all that happened |
| 99213 | Low MDM | 20+ minutes | 19 minutes billed by time, no low MDM to fall back on |
| 99214 | Moderate MDM (2 of 3 elements) | 30+ minutes | Only one moderate element documented |
| 99215 | High MDM (2 of 3 elements) | 40+ minutes | High risk not shown in the assessment and plan |
E/M in behavioral practices: PMHNPs, psychiatrists and add-on psychotherapy (90833, 90836, 90838)
When a psychiatrist or psychiatric nurse practitioner (PMHNP) manages medication and also provides psychotherapy at the same visit, the claim carries an E/M code plus a psychotherapy add-on: 90833, 90836 or 90838. The Medicare contractor WPS's billing and coding article A57480 (Psychiatry and Psychology Services, revision effective January 1, 2026) sets four rules for the pair:
- The E/M level comes from MDM. The article says time may not be used as the basis of E/M code selection.
- The times never overlap. Time spent on the E/M activities is not included in the psychotherapy time.
- Both services must stand on their own. They must be significant and separately identifiable, although a separate diagnosis is not required.
- No prolonged services. Prolonged service codes may not be reported with 90833, 90836 or 90838.
A commercial plan can say the same thing. Kaiser Permanente Washington's behavioral health add-on policy (commercial and Medicare plans, effective March 1, 2024) has the E/M code selected on the level of work, not time, requires the documented time to match the code billed, and says the two services' time cannot overlap.
Picking the add-on by psychotherapy minutes
The add-on is chosen only by the psychotherapy minutes, after the E/M work is set aside. A North Carolina Psychiatric Association presentation on the psychotherapy codes gives the ranges: 90833 for 16-37 minutes, 90836 for 38-52 and 90838 for 53 or more. The table pairs each add-on with 99214, at the 2026 national Medicare amount (unadjusted), office.
Who can bill the pair
Medicare pays E/M services billed by nurse practitioners, clinical nurse specialists, certified nurse midwives and physician assistants when the service is within their state scope of practice (chapter 12, section 30.6.1), so a PMHNP can bill 99214 with 90833 when the note supports both. Chapter 12 also states that clinical psychologists and clinical social workers cannot bill Medicare for psychotherapy that includes medical E/M services. Those clinicians bill psychotherapy codes without an E/M base. Our behavioral health billing page describes how we take over this claim mix, psychiatric prescribers included.
| Claim lines | Psychotherapy minutes (E/M time excluded) | E/M level set by | 2026 national Medicare amount (unadjusted), office, both lines |
|---|---|---|---|
| 99214 + 90833 | 16-37 | MDM only | $135.61 + $81.50 = $217.11 |
| 99214 + 90836 | 38-52 | MDM only | $135.61 + $103.21 = $238.82 |
| 99214 + 90838 | 53 or more | MDM only | $135.61 + $136.61 = $272.22 |
| 99213 + 90833 | 16-37 | MDM only | $95.19 + $81.50 = $176.69 |
Preventive counseling 99401-99404 and when therapists can't use them
CPT 99401-99404 report face-to-face preventive counseling and risk-factor reduction for a person without a specific illness that the counseling would treat. Healthy Blue's behavioral counseling for prevention policy (CAM 086HB, reviewed April 1, 2026) lists the four codes at approximately 15, 30, 45 and 60 minutes, so 99404 is the hour-long session. The same policy says the codes are not for counseling patients with symptoms or established illness; those visits take the appropriate office, hospital, consultation or other E/M codes. It also requires record review for 99402-99404.
Why a therapy practice usually cannot use them
Three rules close these codes to most therapy claims:
- The patient is already in treatment. A therapy client has a diagnosis the sessions treat, which is exactly the case the preventive codes exclude.
- Medicare does not cover them. All four carry status N (non-covered) in the 2026 relative value file, so no Medicare payment amount exists.
- The therapist's Medicare benefit is treatment. CMS's page for marriage and family therapists and mental health counselors describes their benefit as services for the diagnosis and treatment of mental illnesses, paid at 75% of the clinical psychologist amount.
Chapter 12 also bars Medicare payment for E/M codes billed by physical or occupational therapists in independent practice. A commercial plan may cover 99401-99404 for its own members, so check that plan's preventive policy and the clinician types it accepts before billing them.
| Code | Approximate counseling time (Healthy Blue CAM 086HB) | Medicare 2026 status | Fits a therapy client in treatment? |
|---|---|---|---|
| 99401 | 15 minutes | N: non-covered | No: use the treatment code that fits |
| 99402 | 30 minutes | N: non-covered | No: use the treatment code that fits |
| 99403 | 45 minutes | N: non-covered | No: use the treatment code that fits |
| 99404 | 60 minutes | N: non-covered | No: use the treatment code that fits |
Consults and inpatient codes (99252-99255) for specialists
Consult codes are the E/M family most likely to be billed to a payer that does not recognize them. MLN006764 says Medicare does not recognize the inpatient consultation codes 99252-99255 or the office consultation codes 99242-99245 for Part B payment; the practitioner reports the E/M visit code that fits instead. Medicare does pay the telehealth consultation codes G0406-G0408 and G0425-G0427. Commercial plans set their own consult policy, so a specialist practice keeps a payer list showing which plans take consult codes and which want the visit code.
For a Medicare patient seen at a hospital's request, the visit code depends on the setting: initial hospital inpatient or observation care is 99221-99223 and subsequent care is 99231-99233 (MLN006764). Patients admitted and discharged on the same date take 99234-99236 when the stay is 8 hours or more. Hospital codes count time per calendar date.
CPT 99254 and the inpatient consult ladder
Under the AAFP table, 99252 is straightforward MDM or 35 minutes, 99253 low or 45, 99254 moderate or 60, and 99255 high or 80. For Medicare the same moderate-complexity first hospital visit is billed as 99222, with a 2026 national Medicare amount (unadjusted), facility, of $116.90.
Code guides for specialist visits
Specialist claims often pair an E/M visit with a test or procedure. Our code guides for those pairs: EKG CPT codes 93000 and 93010, urology CPT codes, EGD CPT codes, IV push codes 96374 and 96375, and modifiers 52, 53 and 59.
| Consult code | MDM level | Or total time (at least) | Medicare 2026 | What Medicare takes instead |
|---|---|---|---|---|
| 99252 | Straightforward | 35 minutes | Not recognized (status I) | Initial hospital or observation visit, 99221-99223, by level |
| 99253 | Low | 45 minutes | Not recognized (status I) | Initial hospital or observation visit, 99221-99223, by level |
| 99254 | Moderate | 60 minutes | Not recognized (status I) | 99222 at moderate MDM ($116.90 facility) |
| 99255 | High | 80 minutes | Not recognized (status I) | 99223 at high MDM ($156.32 facility) |
| 99242-99245 (office) | Straightforward to high | 20 to 55 minutes | Not recognized (status I) | Office visit 99202-99215 for the patient type and level |
Modifier 25 and same-day procedures
Modifier 25 lets an E/M visit be paid on the same day as a procedure when the visit is a significant, separately identifiable service above and beyond the procedure's usual pre- and post-operative work. Chapter 12, section 30.6.6 sets the Medicare rules:
- Modifier 25 goes on the E/M code, never on the procedure.
- The same physician or qualified non-physician practitioner provides both services to the same patient on the same day.
- Different diagnoses are not required, but both the E/M and the procedure must be documented in the record.
- A Medicare contractor that finds a group's modifier 25 use high may add prepayment screens or documentation requirements after a case-by-case review.
- Modifier 25 cannot generate payment for two E/M visits on the same day by the same physician.
Modifier 25 and G2211
Medicare does not pay G2211 when its base visit carries modifier 25, except when the same practitioner also provides an annual wellness visit, vaccine administration or any Part B preventive service that day (MLN006764). G2211 adds $17.37 at the 2026 national Medicare amount (unadjusted), office.
Modifier 57: the decision for surgery
For a procedure with a 90-day global period, an E/M on the day of or the day before the procedure is paid when modifier 57 shows the visit resulted in the decision to operate. Medicare does not pay a modifier 57 visit before a procedure with a 0- or 10-day global period (section 30.6.6). A same-day test such as an EKG has its own billing rules, and a procedure stopped early takes a reduced-service modifier such as modifier 52 rather than a modifier on the visit.
| Same-day situation | What goes on the claim (Medicare) | Source |
|---|---|---|
| Minor procedure plus a separate problem worked up and managed | E/M with modifier 25, plus the procedure | CPM ch. 12, 30.6.6 |
| Minor procedure, visit only covers the usual pre-procedure work | Procedure only | CPM ch. 12, 30.6.6 |
| E/M with modifier 25 and G2211, no preventive service that day | Drop G2211; it is not paid | MLN006764 |
| E/M with modifier 25, G2211 and an annual wellness visit or vaccine | G2211 may be billed | MLN006764 |
| Visit the day before a 90-day global surgery that decides to operate | E/M with modifier 57 | CPM ch. 12, 30.6.6 |
E/M audit risks for small practices
E/M levels are where Medicare's reviewers find the most money. The CMS 2025 Medicare Fee-for-Service Supplemental Improper Payment Data, covering claims submitted July 1, 2023 through June 30, 2024, projects $3,265,045,695 in improper payments across E/M codes, a 10.1% improper payment rate. Incorrect coding is half of it: 50.0%. In the office family, 99214 carries the largest projected improper payment, and the improper payment rate climbs with the level: 2.1% for 99213, 5.0% for 99214 and 14.8% for 99215.
One-level coding differences, where the record supports a level one step away from the one billed, account for $238,758,920 of the 99214 projection on their own. For a small practice the risk is a pattern, not one claim: a template that pre-fills a high level, a habit of billing by time without recording the minutes, or a new-patient code used for a same-specialty patient seen within 3 years.
A five-point E/M self-check
- Pull 10 visits per clinician at each of 99213, 99214 and 99215.
- For each, confirm the note shows either two MDM elements at the billed level or a recorded total time that meets the full threshold.
- Check every new-patient code against the 3-year, same-specialty history.
- Check every modifier 25 visit for a separately documented problem, and every G2211 for a modifier 25 conflict.
- For psychiatric visits, check that the psychotherapy minutes are recorded separately from the E/M work.
Practices that would rather hand this off can send it to our medical coding service: We check every code against your clinician's documentation and never change a code without the clinician's sign-off. It also runs inside our medical billing services for small practices and our family practice medical billing. To see which unpaid E/M claims are closest to a filing deadline first, Get my free A/R Deadline Map: Clock starts with your claim-level aging export and signed BAA; above 10 requests in a week, we confirm your date within 1 business day.
| Office code | Projected improper payments | Improper payment rate | Incorrect coding share |
|---|---|---|---|
| 99213 | $101,291,185 | 2.1% | 88.4% |
| 99214 | $459,838,842 | 5.0% | 62.5% |
| 99215 | $245,231,199 | 14.8% | 72.5% |
| 99204 | $86,479,262 | 5.4% | 94.9% |
| 99205 | $53,926,227 | 11.1% | 100.0% |
Common questions
- What is CPT code 99213?
- 99213 is the established-patient office or outpatient visit at low complexity. It is met by low medical decision making or at least 20 minutes of the billing clinician's total time on the date of the visit, and Medicare requires the full 20 minutes when time sets the level (CMS chapter 12). Its 2026 national Medicare amount (unadjusted) is $95.19 in the office.
- What is the difference between 99213 and 99214?
- One MDM level or 10 minutes. 99213 needs low MDM or 20 minutes; 99214 needs moderate MDM, meaning two of the three MDM elements at moderate, or 30 minutes. At the 2026 national Medicare amount (unadjusted), office, 99214 is $135.61 against $95.19 for 99213.
- How many minutes is 99215?
- At least 40 minutes of the clinician's total time on the date of the visit, or high MDM (AAFP). Medicare's table runs 99215 from 40 to 54 minutes; from 69 to 83 minutes, Medicare adds one unit of G2212 for prolonged time, and one more unit for each further 15 minutes.
- Can a PMHNP bill 99214 with 90833?
- Yes, when the note supports both. Medicare pays nurse practitioners for E/M services within their state scope of practice, and the WPS article A57480 allows an E/M plus a psychotherapy add-on when the two are significant and separately identifiable. The 99214 level must come from MDM, and 90833 needs 16-37 psychotherapy minutes that do not include the E/M time.
- What is CPT 99404 used for?
- Preventive counseling and risk-factor reduction for a person without an illness the counseling would treat, at approximately 60 minutes (Healthy Blue policy CAM 086HB). Medicare lists 99404 as non-covered in 2026, and a patient with symptoms or a diagnosed condition takes an E/M or treatment code instead.
- What is CPT code 99205 used for?
- A new-patient office visit at high complexity: high MDM or at least 60 minutes of total time. A new patient is one with no E/M or other face-to-face service from the clinician or a same-specialty colleague in the group in 3 years. Its 2026 national Medicare amount (unadjusted) is $236.81 in the office, and CMS's 2025 improper payment data put its improper payment rate at 11.1%.
Sources and review
Page revised November 4, 2026 · Review contact: Hyder Shah (inquiries@claimpillar.com). Every source below was retrieved on November 4, 2026. Medicare amounts come from the CMS CY 2026 relative value file (RVU26D) in our national PFS dataset. CPT codes are AMA property; the descriptions on this page are our own summaries.
- CMS MLN006764: Evaluation and Management Services (May 2026)
- CMS Medicare Claims Processing Manual, Chapter 12 (sections 30.6.1, 30.6.6, 30.6.7, 120)
- AAFP: Time and medical decision making levels for E/M CPT codes
- American College of Surgeons: Medical decision making (office/outpatient E/M)
- WPS billing and coding article A57480: Psychiatry and Psychology Services (rev. effective January 1, 2026)
- Kaiser Permanente Washington: Behavioral health add-on codes payment policy (effective March 1, 2024)
- North Carolina Psychiatric Association: coding for psychotherapy services (2013)
- Healthy Blue: Behavioral counseling for prevention, CAM 086HB (reviewed April 1, 2026)
- CMS: Marriage and family therapists and mental health counselors
- CMS: 2025 Medicare Fee-for-Service Supplemental Improper Payment Data