Who our mental health billing service is for
Our mental health billing service is built for therapists, counselors, psychologists and psychiatric practices: solo clinicians, groups of 2–5 clinicians or 6–15 clinicians, and mixed practices where psychiatric prescribers, psychologists and therapists bill together. Larger groups get a written quote; see the rate card.
Hand your billing to us at moments like these:
- Your biller left and weeks of signed therapy notes have no claim behind them.
- Claims keep returning for session times that do not support the code, or psychiatry visits missing the therapy add-on their notes support.
- A behavioral carve-out such as Optum is rejecting sessions filed after its window.
- You are adding LCSWs, MFTs or counselors who are not yet enrolled with Medicare or your commercial panels.
What we take over and what your practice keeps
We take each behavioral claim from signed note to posted payment; your clinicians keep clinical decisions, the schedule and the patient relationship. We check every code against your clinician's documentation and never change a code without the clinician's sign-off. New patients and changed coverage get behavioral benefits checks. ABA programs run on different codes and authorization cycles, so they bill under our ABA therapy billing service.
| Claim type or task | What we do | What you keep |
|---|---|---|
| Individual, family and group therapy | Code each session from the documented psychotherapy minutes; query notes with no time | Your clinician signs the note and owns the time record |
| Diagnostic evaluations | Check each evaluation against the payer's frequency limits before it goes out | The clinical assessment |
| Psychiatry medication visits | Bill the E/M visit plus the psychotherapy add-on when the note documents separate therapy time, with the two times kept apart | Medical decisions and prescribing |
| Psychological testing | Track the authorization; bill evaluation and test administration time separately | Test selection and the report |
| Telehealth sessions | Set the place of service and modifier each payer requires for the documented session setting | Choosing video, audio-only or in-person care |
| Eligibility and authorizations | Check behavioral benefits for new patients and changed coverage; track authorization expiry dates | Requesting authorizations, with the clinical justification in each |
| Denials and appeals | Work each denial: resubmit, appeal or return it with the fix | Answering documentation questions |
| Posting and patient statements | Post ERAs, calculate patient balances, send statements in your name | Payment plans and hardship decisions |
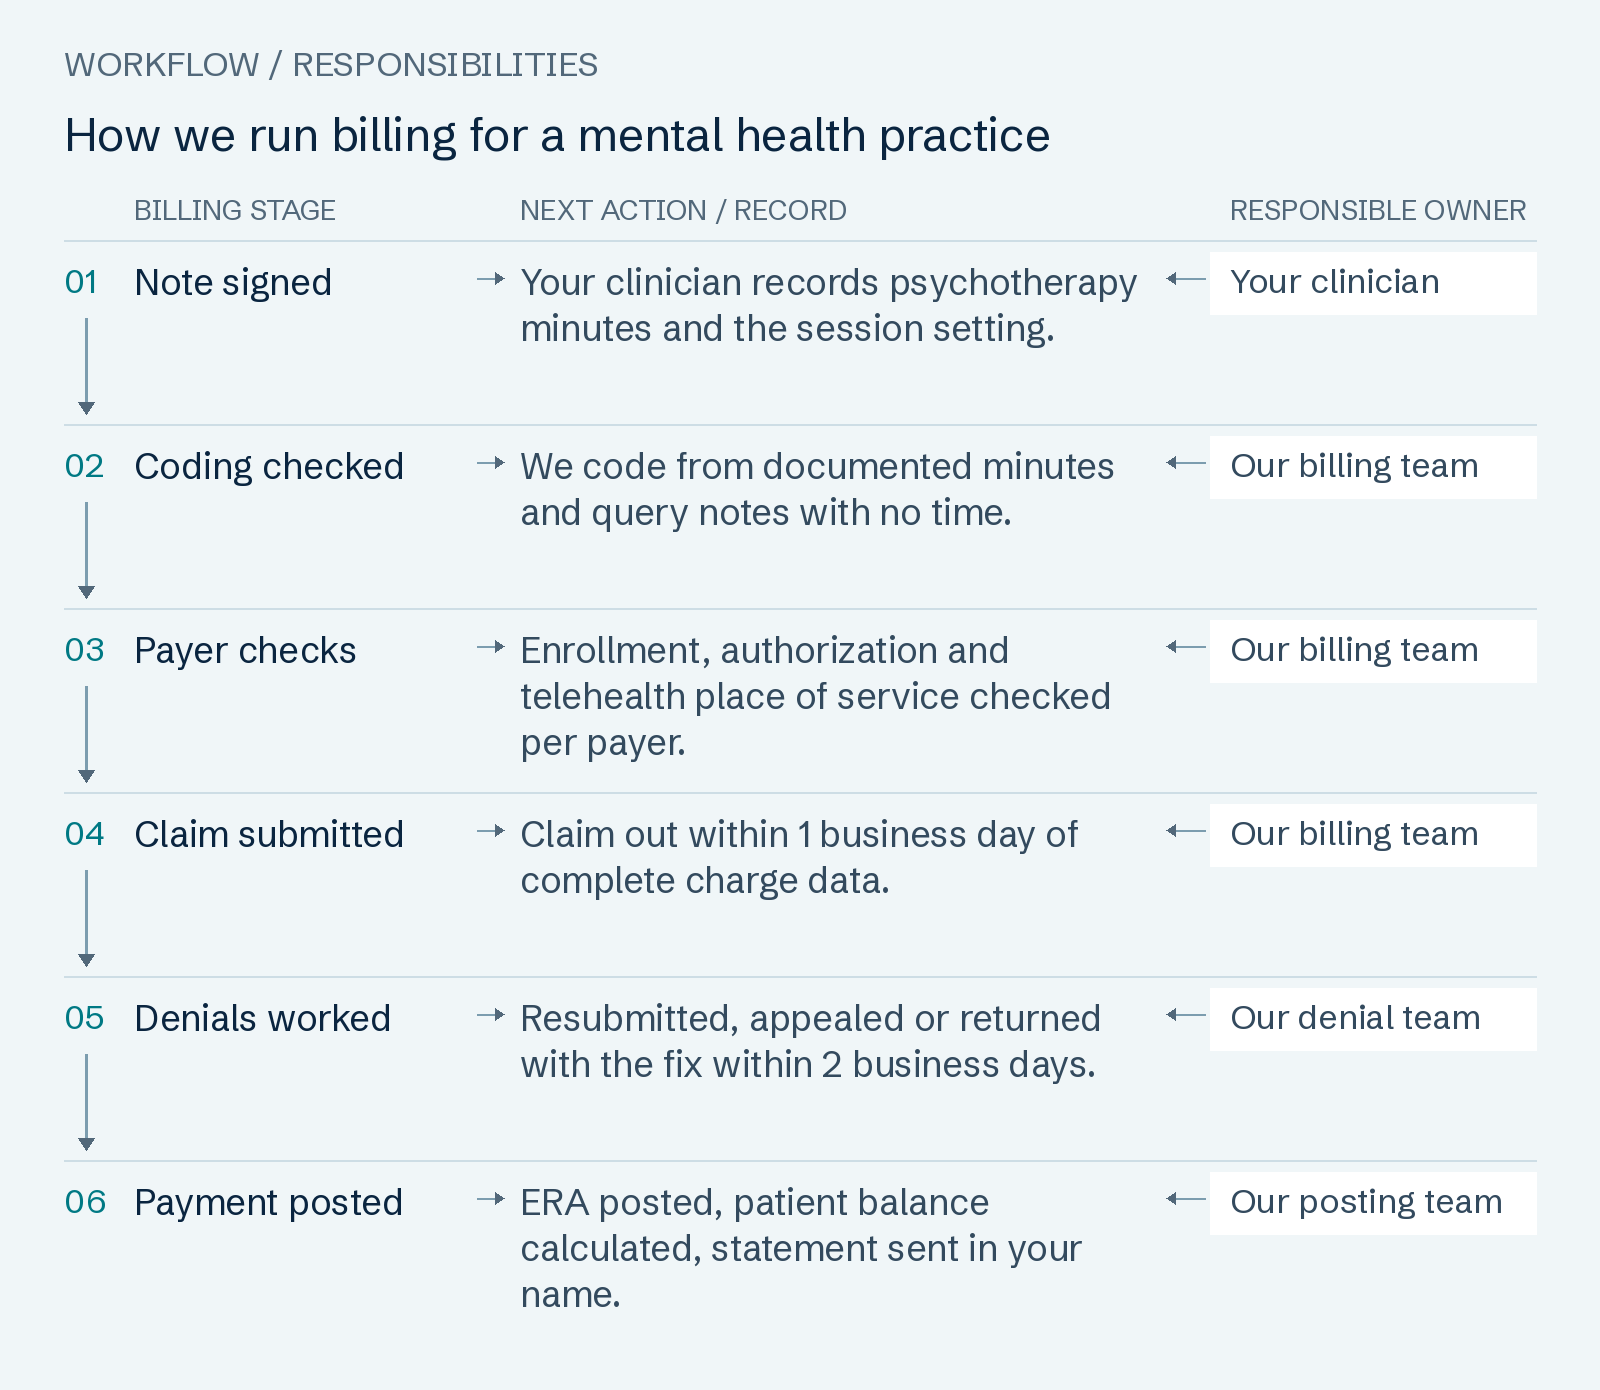
Read the workflow as text
- Note signed — Your clinician records psychotherapy minutes and the session setting. Owner: Your clinician.
- Coding checked — We code from documented minutes and query notes with no time. Owner: Our billing team.
- Payer checks — Enrollment, authorization and telehealth place of service checked per payer. Owner: Our billing team.
- Claim submitted — Claim out within 1 business day of complete charge data. Owner: Our billing team.
- Denials worked — Resubmitted, appealed or returned with the fix within 2 business days. Owner: Our denial team.
- Payment posted — ERA posted, patient balance calculated, statement sent in your name. Owner: Our posting team.
Where mental health practices lose revenue, and what we do about it
Behavioral claims fail on session time, code pairing, clinician enrollment and setting. Palmetto GBA reports that an HHS-OIG review found almost half of the Medicare psychotherapy services it examined were inappropriate: not covered, inadequately documented or medically unnecessary. We check the billing, authorization, enrollment and deadline details below. Questions about clinical support go back to your clinician; clinical decisions stay with them.
- Session time that does not support the code. Psychotherapy is coded by documented minutes, and 90837 needs 53 minutes or more, so a standing 50-minute hour does not reach it. We code from the minutes in the note and query your clinician when no time is recorded.
- Psychiatry visits billed as one service. Medication management with therapy is an E/M visit plus a psychotherapy add-on, and WPS billing article A57480 keeps E/M time out of the therapy minutes. When the note documents separate therapy time, we bill both lines and keep the two times apart.
- Clinicians billed under the wrong enrollment. CMS does not allow services to be billed incident to a clinical social worker, MFT or mental health counselor. We bill each clinician under their own enrollment; enrolling new clinicians is covered under credentialing below.
- Short carve-out filing windows. Optum Behavioral Health requires claim information within 90 calendar days of the date of service. We work inherited claims nearest deadline first and submit new claims once charge data is complete.
- Testing booked without an authorization. The same Optum manual says psychological testing and intensive outpatient care typically need prior authorization, while routine outpatient therapy usually does not. We track each authorization's expiry against your schedule.
- Telehealth billed with the wrong setting. Medicare uses POS 10 when the patient is at home and POS 02 elsewhere; commercial plans set their own telehealth policies. We apply each payer's current policy to every telehealth claim.
When denials are already stacking up, our denial management team starts with the nearest deadlines.
What mental health billing services cost with us
Full-Service Billing for mental health practices is priced by practice size. The percentage applies to insurance payments only: 0% of patient payments and copays. Example: 3 therapists with $30,000 of insurance payments in a month pay 7.5%, or $2,250. That month's cap would be $2,700.
- Setup: $0.
- Minimum: $400 a month. Invoices 1–3: only percentage fees on that month's insurance payments, plus any statements or add-ons you order; the $400 minimum starts with invoice 4.
- Cap: Percentage fees and mailed statements are capped at 9.0% of that month's insurance payments; the $400 minimum still applies from invoice 4.
- Multi-specialty practices: each clinician's claims are billed at that clinician's segment rate; the size band counts every clinician.
- Contract: Month to month. Leave with 30 days' written notice. No termination fee.
The full rate card and fee terms list what is excluded from the fee base. To price the switch against your own claims first, request The Free A/R Deadline Map: every unpaid insurance claim over 90 days in the aging report you send, with its amount and the deadline it faces, in 5 business days. Clock starts with your claim-level aging export and signed BAA; above 10 requests in a week, we confirm your date within 1 business day.
| Practice size | Rate for mental and behavioral health | Charged on |
|---|---|---|
| 1 clinician | 8.0% | Insurance payments only (0% of patient payments) |
| 2–5 clinicians | 7.5% | Insurance payments only (0% of patient payments) |
| 6–15 clinicians | 7.0% | Insurance payments only (0% of patient payments) |
How we start: switching from in-house billing or another company
Go-live, when your first claims go out, comes within 5 business days of access; any unbilled backlog follows within 10 business days of access. Clock starts with your signed agreement, signed BAA and working system logins; it extends day for day while we wait on access.
The One-Week Deadline Sweep for Specialty Practices: Every inherited claim within 30 days of a filing, corrected-claim or appeal deadline is worked within 5 business days of access. Starts at access; covers up to 250 claims (more gets a day-1 deadline schedule); worked means submitted, corrected, appealed or returned with the fix. With Optum Behavioral Health's 90-day filing window, that first week decides whether an inherited session still gets paid.
- You sign the agreement and BAA and send logins to your practice-management system and clearinghouse.
- We pull open claims and sort them by filing, corrected-claim and appeal deadline.
- Near-deadline claims are worked first; finished sessions with no claim are billed next.
- Your clinicians answer our documentation questions, such as a missing session time or telehealth setting.
What we need from you: Sign the service agreement and BAA, give us logins to your practice-management system and clearinghouse, join one 45-minute kickoff call, sign off encounters so charges are complete, and answer our documentation questions within 5 business days. The handoff plan for changing billing companies lists what to request from your current biller.
What we report, and the guarantees behind it
Payments posted within 2 business days of the remittance, emails answered within 1 business day, and the KPI report with written definitions by the 10th.
On-Our-Watch Guarantee: If a claim misses a filing, corrected-claim or appeal deadline while it is on our watch, we pay you what it would have paid. Claims we get complete 10+ business days before the deadline; contracted rate less any copay you collected, paid automatically within 30 days of final denial; capped $10,000/month; your holds excluded.
Clock-or-Credit Guarantee: From go-live, every new claim goes out within 1 business day of complete charge data, and every denial is worked within 2 business days of posting — or $25 comes off your invoice for each late one. Mon–Fri ET business days by your system's timestamps; worked: resubmitted, appealed or returned with the fix; auto-credited; capped at monthly fee; clearinghouse outages excluded.
We cannot make a payer approve a session; what we guarantee is the deadlines and clocks we control. We publish client results only with written permission. Until we have them, judge us by the guarantees and the free Deadline Map. Questions before you start go to our team.
Systems, credentialing and privacy for your practice
We work inside your existing practice-management system and clearinghouse; tell us which ones and we confirm in writing within 1 business day. EHR compatibility details.
Which of your clinicians we can bill Medicare for
We bill Medicare for psychiatrists, clinical psychologists, clinical social workers, nurse practitioners and physician assistants, and for marriage and family therapists and mental health counselors (including LPCs), who may enroll in Medicare and bill independently since January 1, 2024. Each clinician needs their own enrollment first. Credentialing & Payer Enrollment costs $149 per payer. Billed only after the payer confirms your effective date; $0 if denied or panel closed; filed within 5 business days of your complete packet.
What records we ask for, and what stays private
We bill from the progress note and time record, never from psychotherapy notes. HHS says psychotherapy notes typically are not required for payment, and it excludes session start and stop times and summaries of diagnosis and progress from them, so what a claim needs typically sits outside your clinicians' private notes. Every engagement starts with a signed BAA.
Common questions
- How much do mental health billing services cost with you?
- 8.0% of insurance payments for 1 clinician, 7.5% for 2–5 clinicians and 7.0% for 6–15 clinicians, with 0% of patient payments and $0 setup. Ask any company you compare whether its percentage also takes a share of copays. See the rate card and our guide to medical billing costs.
- How much do mental health billers charge compared with hiring one?
- A billing and posting clerk's median wage is $48,500 a year (BLS, May 2025): about $4,042 a month before benefits, software and the clearinghouse, or about $5,774 at the private-industry benefit share (BLS, June 2026). Our behavioral rate runs from 7.0% to 8.0% of insurance payments, with 0% of patient payments.
- Do you bill psychiatry medication visits that include therapy?
- Yes. We bill the E/M visit plus the psychotherapy add-on the therapy minutes support, and keep E/M time out of those minutes, as WPS billing article A57480 requires. Your prescriber keeps every medical decision.
- Can your team bill Medicare for our LCSWs, MFTs and counselors?
- Yes, once each one is enrolled. MFTs and mental health counselors may enroll in Medicare and bill independently since January 1, 2024, per CMS booklet MLN1986542, and we bill every LCSW, MFT and counselor under their own enrollment. We file the enrollments through Credentialing & Payer Enrollment. Billed only after the payer confirms your effective date; $0 if denied or panel closed; filed within 5 business days of your complete packet.
- Is there a long-term contract?
- Month to month. Leave with 30 days' written notice. No termination fee. Clean-Exit Terms: Notice by email; optional run-out covers claims we submitted before your exit date, at your plan rate; handover file within 10 business days of exit.
- How fast can we switch billing companies?
- Go-live, when your first claims go out, comes within 5 business days of access; any unbilled backlog follows within 10 business days of access. Clock starts with your signed agreement, signed BAA and working system logins; it extends day for day while we wait on access.
- Do you work in our EHR and practice-management system?
- We work inside your existing practice-management system and clearinghouse; tell us which ones and we confirm in writing within 1 business day. You keep your system and clearinghouse account, and their fees stay with those vendors (see the rate card).
Sources and review
Page revised October 10, 2026 · Review contact: Hyder Shah (inquiries@claimpillar.com). The workflow checklists are editorial recommendations; payer requirements depend on the program and current policy.
- Palmetto GBA: Psychotherapy Services (JM Part B, published 02/23/2026)
- CMS MCD: Billing and Coding: Psychiatry and Psychology Services (A57480, WPS J5/J8)
- CMS MLN1986542: Medicare & Mental Health Coverage (March 2026)
- CMS Telehealth FAQ (updated 02/26/2026)
- Optum Behavioral Health National Provider Network Manual (effective 09/01/2026)
- HHS: Extra HIPAA protections for psychotherapy notes