EGD CPT code basics: 43235 diagnostic
43235 is the diagnostic EGD: the endoscopist examines the esophagus, stomach and duodenum and does nothing else. Every therapeutic EGD code builds on it. The CMS CY 2026 relative value file (RVU26D) lists 43235 as the endoscopic base code for 43239, 43248, 43249, 43251 and the rest of the family, and gives those codes multiple-procedure indicator 3, the endoscopy pricing rule covered under 43239 below. The code numbers and our plain-word summaries are all this page uses; the official descriptors belong to the AMA's CPT code set.
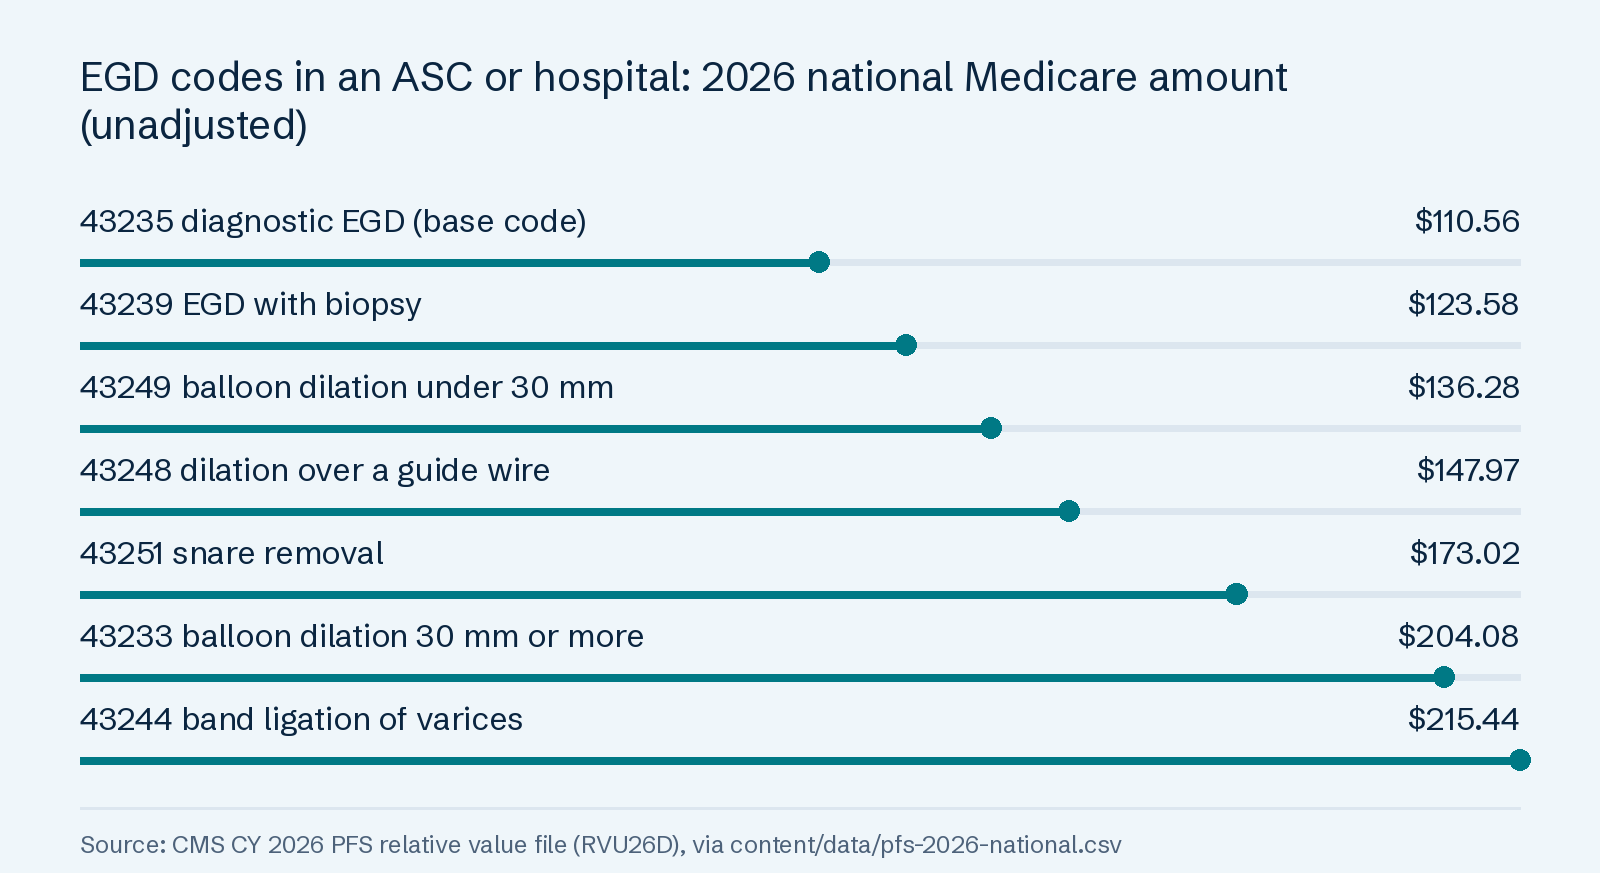
The table shows each code's 2026 national Medicare amount (unadjusted) from RVU26D. "Office" is the non-facility amount (POS 11). "ASC or hospital" is the facility amount, which Claims Processing Manual chapter 12, section 20.4.2 applies in an off-campus or on-campus hospital outpatient department (POS 19 or 22) and a Medicare-participating ASC (POS 24). Actual payment varies by locality, setting and payer. 43233 and 43244 have no office amount: RVU26D publishes a facility amount only.
What one EGD code already includes
The 2026 NCCI policy manual, chapter VI folds several services into the scope itself:
- A surgical endoscopy includes the diagnostic endoscopy, so 43235 is never billed with a surgical EGD code.
- Esophageal and gastric washings for cytology are part of the EGD.
- Control of bleeding during the procedure is not separately reportable.
- Fluoroscopy (76000) is integral to every endoscopic procedure and is not billed with it.
| Code | Our plain-word summary | 2026 Medicare: office | 2026 Medicare: ASC or hospital | Unit check |
|---|---|---|---|---|
| 43235 | Diagnostic EGD, no intervention | $322.65 | $110.56 | Drop it when any surgical EGD code is billed |
| 43239 | EGD with one or more biopsies | $418.85 | $123.58 | One unit per session |
| 43248 | EGD dilation over a guide wire | $457.93 | $147.97 | One unit for all strictures |
| 43249 | EGD balloon dilation, under 30 mm | $1,180.39 | $136.28 | One unit for all strictures |
| 43233 | EGD balloon dilation, 30 mm or more | No office amount | $204.08 | One unit for all strictures |
| 43244 | EGD band ligation of varices | No office amount | $215.44 | One unit per session |
| 43251 | EGD snare removal of a lesion | $545.77 | $173.02 | Repeat snares in one region: one unit |
43239: biopsy, single or multiple
43239 is billed once per session, however many biopsies were taken. NCCI chapter VI says that when the same endoscopic procedure is repeated at one encounter in the same region, only one code with one unit of service is reported. Five gastric biopsies and a duodenal biopsy in one EGD are still one line of 43239, and it replaces 43235 rather than joining it. The 2026 NCCI policy manual, chapter I adds that a code whose descriptor covers biopsies in the plural takes one unit however many were taken.
Biopsy plus another EGD technique
When the report shows a biopsy and a different technique, such as a snare removal, chapter VI allows more than one code when no single code describes the work, with modifier 51 on the secondary code. The pair is still edited: the 2026 fourth-quarter NCCI practitioner PTP edits list 43239 as the column-two code under 43251, 43248, 43249 and 43233, modifier indicator 1. Chapter I lets a biopsy be reported beside a removal only when it was taken from a separate lesion, or when its pathology result led straight to the larger procedure on the same lesion. So 43239 next to 43251 needs modifier 59 or XS and a report that names the separate lesion; a lesion biopsied and then snared is 43251 alone. Chapter 12, section 40.6 then prices the pair with the endoscopy rule: the full value of the higher code plus the difference between the next code and the base endoscopy. Illustrative example, not client data, using 2026 facility amounts and assuming the report documents a separate lesion and 43239 carries 59 or XS:
- 43251 snare removal pays in full: $173.02.
- 43239 adds only its difference over 43235: $123.58 minus $110.56 equals $13.02.
- Expected total for the endoscopist: $186.04.
A payment poster who expects 100% plus 50% would look for $234.81 and flag a correct payment as short. Check the base-code math before you appeal.
The biopsy also creates a separate claim you do not send: the pathologist or lab bills its specimen exam (such as 88305) on its own claim, and its units follow the pathology code's own rules, not the number of 43239 lines.
Dilation, banding and snare codes
The dilation code depends on the method in the report: 43249 for a balloon under 30 mm, 43233 for a balloon of 30 mm or larger, and 43248 for dilators passed over a guide wire.
Dilation takes one unit
NCCI chapter VI says a GI endoscopy dilation code includes every stricture dilated during the procedure and is not reported with more than one unit. If a non-endoscopic dilation such as 43450 or 43453 fails and the endoscopist then dilates through the scope, only the endoscopic dilation is reported. In the office, 43249 carries $1,180.39 against $136.28 in an ASC or hospital, the widest site gap in the table, so a wrong place of service on a 43249 line moves the expected payment by more than $1,000.
Banding and snare removal
- 43244, band ligation of varices, has a facility amount only ($215.44). Because chapter VI makes control of bleeding integral to an endoscopic procedure, a separate bleeding-control code is not added for bleeding the banding treats in the same session. A return to the endoscopy suite on the same date for bleeding is a separate encounter: chapter VI allows the bleeding-control code with modifier 78.
- 43251, snare removal, is billed once for repeat snares in one region under the same-region rule. A biopsy of a different lesion in the same session can still be billed as 43239 with modifier 59 or XS beside 43251 when the report documents the separate lesion.
EGD and colonoscopy on the same day
An EGD and a colonoscopy belong to different endoscopy families (base codes 43235 and 45378), so chapter 12, section 40.6 treats them as unrelated endoscopies and applies the usual multiple-surgery rules: 100% of the higher-valued code and 50% of the next. When one family has two codes, the endoscopy rule prices that family first and its total counts as one service before the 100% and 50% split.
If the colonoscopy started as a Medicare screening, the colonoscopy code takes modifier PT. Claims Processing Manual chapter 18, section 60 says that for dates of service in 2023 through 2026, PT on a converted screening waives the deductible and sets coinsurance at 15% for the qualifying codes on that claim.
Same-session claim example
Illustrative example, not client data. In an ASC (POS 24), the endoscopist biopsies the stomach during an EGD and removes a colon polyp by snare during a diagnostic colonoscopy. The professional claim, using 2026 national facility amounts (unadjusted):
| Line | Code | Facility amount | Payment step | Expected |
|---|---|---|---|---|
| 1 | 45385 colonoscopy, snare removal | $223.45 | Higher-valued service: 100% | $223.45 |
| 2 | 43239-51 EGD with biopsy | $123.58 | Second service: 50% | $61.79 |
| Total | Endoscopist's claim | $285.24 |
Anesthesia and facility claims for one EGD
One EGD in an ASC or hospital produces up to four claims from different billers. The map below shows who sends each, on which claim format, and the rule that most often trips it.
Anesthesia: one line for the whole session
Anesthesia for an EGD alone is 00731, and anesthesia for an EGD and colonoscopy in one session is 00813; both carry 5 base units in the CMS anesthesia base unit file, which CMS lists as unchanged for 2026. 00813 covers both scopes in one session, so the anesthesia biller sends one 00813 line with the combined minutes, not 00731 plus a colonoscopy anesthesia code. That matches chapter 12, section 50, which pays anesthesia for multiple procedures on the highest base unit plus the total anesthesia time. If your group handles that claim, our anesthesia billing service covers it.
Facility claims: ASC vs hospital outpatient
Chapter 14 has an ASC bill Medicare on the 837 professional format (CMS-1500 in rare cases) with POS 24, and ASCs have not needed modifier SG on Medicare facility claims since January 1, 2008. A hospital outpatient department bills on the 837 institutional format or Form CMS-1450 under chapter 4.
| Claim | Who sends it | Format | Codes for one EGD | Check before sending |
|---|---|---|---|---|
| Professional | Endoscopist's practice | 837P / CMS-1500 | 43235 family code; POS 19, 22 or 24 | POS matches the site so the facility amount applies |
| Anesthesia | Anesthesia group or CRNA | 837P / CMS-1500 | 00731, or 00813 with a colonoscopy | One line, total minutes, highest base unit |
| ASC facility | The ASC | 837P / CMS-1500 | The same procedure code, POS 24 | No SG modifier for Medicare |
| Hospital outpatient facility | The hospital | 837I / CMS-1450 | The procedure code on the institutional claim | Type of bill 13X |
| Pathology | Pathologist or lab | 837P / CMS-1500 | Specimen exam such as 88305 | Billed apart from the EGD lines |
Prior auth and diagnosis pairing
Original Medicare's national prior authorization programs do not list EGD. The hospital outpatient prior authorization program covers blepharoplasty, botulinum toxin injections, panniculectomy, rhinoplasty, vein ablation, implanted spinal neurostimulators, cervical fusion with disc removal and facet joint interventions. The ASC prior authorization demonstration, phased in from January 2026 in ten states, targets the first five of those categories. Medicare Advantage and commercial plans sit outside these programs and may set their own requirements, so check the patient's plan when the EGD is scheduled, not after. Practices short on staff for that step can hand it to our prior authorization services.
Diagnosis pairing
The FY 2026 ICD-10-CM Official Guidelines, section IV, set three outpatient rules that decide the diagnosis line on an EGD claim:
- Reason first. For outpatient same-day surgery, the reason for the procedure is the first-listed diagnosis, even if the procedure is not performed because of a contraindication.
- No uncertain diagnoses. Do not code a condition documented as "probable", "suspected" or "rule out"; code the signs, symptoms or abnormal findings to the highest degree of certainty instead.
- Postoperative diagnosis when it differs. For ambulatory surgery, code the diagnosis the procedure was performed for; if the postoperative diagnosis is confirmed and differs from the preoperative one, code the postoperative diagnosis, since it is the most definitive.
A pre-procedure visit on the same day by the same physician is normally included in the endoscopy payment under chapter 12; only a significant, separately identifiable visit is billed, and the guide to office visit levels such as 99213 covers how to choose that level.
Common EGD denials
Most repeat EGD denials and short payments come from units, bundling and the place of service, all visible on the claim before it goes out. Fix them at charge entry rather than appealing claim by claim.
If EGD lines keep coming back, our gastroenterology billing services set each case's place of service by where the endoscopist scoped and post each scope line with its adjustment reason; what the service costs is published. To see which unpaid claims are closest to their filing deadlines first, get my free A/R Deadline Map: The Free A/R Deadline Map (Clock starts with your claim-level aging export and signed BAA; above 10 requests in a week, we confirm your date within 1 business day.).
| Problem | Why it denies or underpays | Fix |
|---|---|---|
| 43235 billed with 43239 | A surgical scope includes the diagnostic scope (NCCI ch. VI) | Remove 43235 |
| Two units of 43239 or 43249 | One unit covers all biopsies in a region or all strictures | Bill one unit |
| Second EGD code paid at only its difference | That is the endoscopy pricing rule | Recalculate against 43235 before appealing |
| Office POS on an ASC case | The line prices at the non-facility amount | Correct POS to 24 and send a corrected claim |
| 76000 billed with the EGD | Fluoroscopy is integral to endoscopy (NCCI ch. VI) | Remove 76000 |
| 00731 and a colonoscopy anesthesia code for one session | One anesthetic pays the highest base unit with total time | Bill 00813 with the combined minutes |
| Same-day E/M bundled | The visit is included in the endoscopy payment | Bill a visit only when it is significant and separately identifiable |
Common questions
- What is the CPT code for EGD?
- 43235 is the CPT code for a diagnostic EGD with no intervention. When the endoscopist biopsies, dilates, bands or snares, a code from the 43235 family replaces it. Its 2026 national Medicare amount (unadjusted) is $322.65 in the office and $110.56 in an ASC or hospital (CMS RVU26D).
- What is the difference between 43235 and 43239?
- 43235 is a diagnostic EGD; 43239 is an EGD with one or more biopsies. Because a surgical endoscopy includes the diagnostic one, they are not billed together for one session (NCCI chapter VI). In 2026, 43239 carries $418.85 in the office and $123.58 in an ASC or hospital (national, unadjusted).
- Can 43239 be billed more than once?
- Not for one session. NCCI chapter VI allows one code with one unit of service when the same endoscopic procedure is repeated in the same region at one encounter, so several biopsies are one line of 43239. A biopsy at a separate encounter on the same date is a different case and needs its own documentation.
- How do you bill EGD and colonoscopy together?
- Bill each scope's code on the same claim, with modifier 51 on the secondary code. Medicare treats them as unrelated endoscopies and pays 100% of the higher-valued code and 50% of the next (chapter 12, section 40.6). Anesthesia goes out as one 00813 line with the combined minutes.
- Does an EGD need prior authorization?
- Not under Original Medicare's national programs: neither the hospital outpatient prior authorization list nor the 2026 ASC demonstration includes EGD. Medicare Advantage and commercial plans may set their own requirements, so check the patient's plan when the procedure is scheduled.
Sources and review
Page revised November 5, 2026 · Review contact: Hyder Shah (inquiries@claimpillar.com). Every source below was retrieved and checked on November 5, 2026. Medicare amounts are 2026 national Medicare amounts (unadjusted) from our dataset built on the CMS CY 2026 PFS relative value file (RVU26D); actual payment varies by locality, setting and payer.
- CMS: Medicare NCCI Policy Manual 2026, Chapter VI (digestive system)
- CMS: Medicare NCCI Policy Manual 2026, Chapter I (general correct coding policies)
- CMS: Medicare NCCI procedure-to-procedure (PTP) edits, practitioner, 2026 Q4 (v32.3)
- CMS: Medicare Claims Processing Manual, Chapter 12 (sections 20.4.2, 40.6 and 50)
- CMS: Medicare Claims Processing Manual, Chapter 14 (ambulatory surgical centers)
- CMS: Medicare Claims Processing Manual, Chapter 4 (hospital outpatient)
- CMS: Medicare Claims Processing Manual, Chapter 18, section 60 (colorectal cancer screening)
- CMS CY 2026 PFS relative value files (RVU26D)
- CMS: Anesthesiologists Information Center (base units and 2026 conversion factors)
- CMS: Prior Authorization for Certain Hospital Outpatient Department Services
- CMS: Prior Authorization Demonstration for Certain Ambulatory Surgical Center Services
- CMS: ICD-10-CM Official Guidelines for Coding and Reporting, FY 2026