Who our urgent care billing service is for
Our urgent care billing service is built for independent urgent care centers and walk-in clinics, from one site to multi-location groups of 6–15 clinicians. Our scope fits clinics that run point-of-care tests and X-ray on site, staff evenings and weekends with per-diem clinicians, and see work injuries alongside walk-in illness. Chronic-care visits at the same clinic are billed the way our primary care billing team bills them. A hospital's own facility claim is outside our scope.
Urgent care owners look for outside billing when:
- the biller who knew each payer's urgent care rules has left, and visit lines start coming back unpaid;
- rapid test lines keep rejecting and nobody has time to fix and resubmit them;
- a new site is about to open with no one to set up its billing;
- work-injury visits sit in insurance A/R because they went to the health plan first.
What we take over and what your clinic keeps
We take over urgent care billing from the signed note to the posted payment, for every site and every rendering clinician. We check every code against your clinician's documentation and never change a code without the clinician's sign-off. Eligibility runs through our insurance checks at check-in for new patients and changed coverage, so each claim starts with the right payer. Your clinicians keep treating and signing notes; the workflow figure shows how a month runs.
| Task | What we do | What you keep |
|---|---|---|
| Payer and site setup | Record each payer's urgent care format and each site's place of service and CLIA number. | Your payer contracts and CLIA certificates |
| Visit and procedure coding | Check visit level, modifier 25, laceration, splint and drainage codes against the note. | Final say on every code |
| Injections and drugs | Bill the injection with the drug and units given, and no nurse visit beside it on Medicare claims. | Drug and dose documentation |
| Rapid tests | Check whether the test requires QW and include the testing site's required CLIA information on the claim. | The test menu at each site |
| X-rays | Bill global, technical or professional component by who read the film. | Your radiology read agreement |
| Workers' comp visits | Bill job injuries to the comp carrier first, not the health plan. | The work-injury question at check-in |
| Claims, denials and A/R | Submit within 1 business day, work denials within 2 business days and follow every open insurance balance. | Encounter sign-off by the clinician |
| Posting and patient balances | Post each remittance within 2 business days; send statements in your clinic's name. | Copays collected at the front desk |
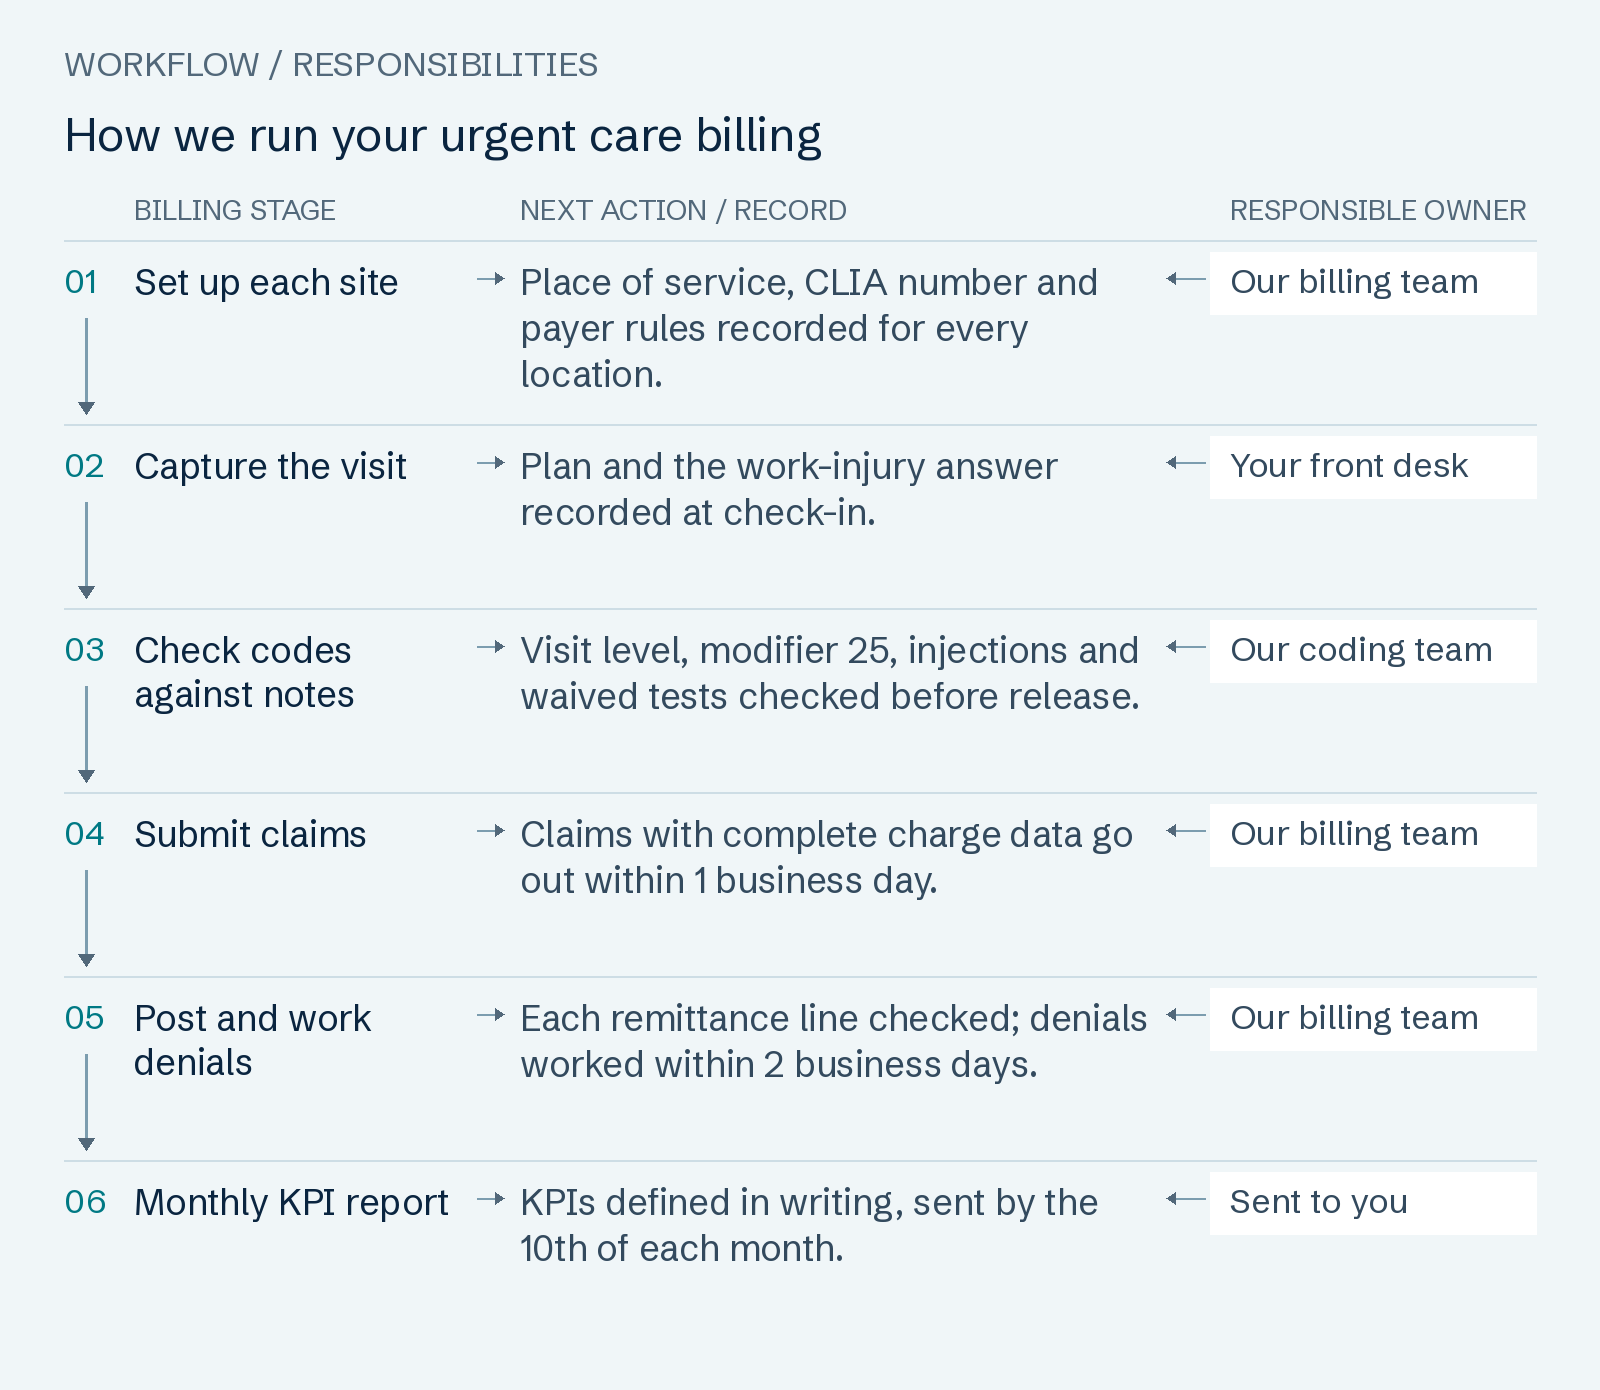
Read the workflow as text
- Set up each site — Place of service, CLIA number and payer rules recorded for every location. Owner: Our billing team.
- Capture the visit — Plan and the work-injury answer recorded at check-in. Owner: Your front desk.
- Check codes against notes — Visit level, modifier 25, injections and waived tests checked before release. Owner: Our coding team.
- Submit claims — Claims with complete charge data go out within 1 business day. Owner: Our billing team.
- Post and work denials — Each remittance line checked; denials worked within 2 business days. Owner: Our billing team.
- Monthly KPI report — KPIs defined in writing, sent by the 10th of each month. Owner: Sent to you.
Where urgent care clinics lose revenue, and what we do about it
Urgent care revenue leaks in small amounts that repeat on every visit of the same type until someone reads the remittances. We check each point below on every claim.
Visit, procedure and injection claims we check
- A global S-code sent to a plan that will not pay it. We record each contracted payer's urgent-care format and check it before choosing an itemized or global visit claim.
- Procedure and injection days the note does not support. We compare the separately documented visit with the procedure and injection record before adding a second service line.
- After-hours codes Medicare bundles. We check your payer contract before adding an after-hours charge so the claim does not assume every plan pays it separately.
Rapid tests, work injuries and hospital-based sites we handle
- Rapid tests without QW or a CLIA number. We match the test menu to each site's CLIA certificate and check whether the specific test requires QW before submission.
- Work injuries billed to the health plan. We use the work-injury information collected at check-in to identify the carrier and route the claim before following the balance.
- A hospital-based site coded as freestanding. We set the place of service site by site at onboarding and check the visit against the location where care occurred.
What our urgent care billing costs
Urgent care centers sit in the Primary care, pediatrics & urgent care row of our rate card, and the number of clinicians we bill for sets the rate. We charge a percentage of insurance payments and 0% of patient payments, so copays and self-pay visit fees your front desk collects never carry our fee. Setup is $0. Per-diem shifts make urgent care rosters move, so the size count is written down: Clinicians are counted on the 1st of each month from the rendering NPIs we billed the month before (for ABA, BCBAs and BCaBAs, not RBTs). Your rate moves with your size band the next month, in either direction.
Invoices 1–3: only percentage fees on that month's insurance payments, plus any statements or add-ons you order. Percentage fees and mailed statements are capped at 9.0% of that month's insurance payments; from invoice 4, the $400 minimum applies even in a month when the cap comes to less. The full rate card lists every segment and add-on.
| Clinic size (rendering clinicians) | Share of insurance payments | Share of patient payments |
|---|---|---|
| 1 clinician | 6.5% | 0% |
| 2–5 clinicians | 6.0% | 0% |
| 6–15 clinicians | 5.5% | 0% |
| 16 or more clinicians | Pricing is by written quote. | 0% |
How we start: taking over from your biller or current billing company
A billing handover puts three kinds of urgent care claims at risk first: rejected test lines, unworked denials and visits never billed. We start with six things from your clinic:
- Our service agreement and a BAA, both signed.
- Practice-management and clearinghouse logins for each site.
- A claim-level aging report, so we can rank inherited claims by deadline on day one.
- The CLIA certificate for each site and the list of tests each site runs.
- Your payer contracts, or each payer's urgent care fee schedule.
- One 45-minute kickoff call with your practice manager.
Go-live, when your first claims go out, comes within 5 business days of access; any unbilled backlog follows within 10 business days of access. Clock starts with your signed agreement, signed BAA and working system logins; it extends day for day while we wait on access. Every inherited claim within 30 days of a filing, corrected-claim or appeal deadline is worked within 5 business days of access. Starts at access; covers up to 250 claims (more gets a day-1 deadline schedule); worked means submitted, corrected, appealed or returned with the fix.
Our billing handoff plan covers the files to request from your current company. Not ready to switch? Request The Free A/R Deadline Map before you sign a service agreement. Clock starts with your claim-level aging export and signed BAA; above 10 requests in a week, we confirm your date within 1 business day.
What we report each month, and the guarantees on your claims
Both guarantees come in writing, terms beside each promise.
- On-Our-Watch Guarantee: If a claim misses a filing, corrected-claim or appeal deadline while it is on our watch, we pay you what it would have paid. Claims we get complete 10+ business days before the deadline; contracted rate less any copay you collected, paid automatically within 30 days of final denial; capped $10,000/month; your holds excluded.
- Clock-or-Credit Guarantee: From go-live, every new claim goes out within 1 business day of complete charge data, and every denial is worked within 2 business days of posting — or $25 comes off your invoice for each late one. Mon–Fri ET business days by your system's timestamps; worked: resubmitted, appealed or returned with the fix; auto-credited; capped at monthly fee; clearinghouse outages excluded.
The monthly KPI report arrives by the 10th of each month, with clean claims, A/R days and net collection rate defined in writing. These are the clocks we report against:
- New urgent care claims submitted within 1 business day of complete charge data.
- Denials worked within 2 business days of posting through our denial management workflow.
- Payments posted within 2 business days of the remittance.
- Emails answered within 1 business day.
We publish client results only with written permission. Until we have them, judge us by the guarantees and the free Deadline Map.
Your systems, new clinicians and data access
We work inside your existing practice-management system and clearinghouse; tell us which ones and we confirm in writing within 1 business day. Our notes on working inside your practice-management system explain how access and logins are set up, and no patient data moves until our BAA is signed.
We check payer enrollment status and effective dates for each new clinician before releasing their claims. While you are a client, New-Clinician Enrollment covers their enrollment: Clinicians who join while you're a client get enrollment filed with up to 5 payers each (the payer decides), with no per-payer fee. For more payers, or to enroll a new site, Credentialing & Payer Enrollment costs $149 per payer. Billed only after the payer confirms your effective date; $0 if denied or panel closed; filed within 5 business days of your complete packet.
Ready to compare? Talk to our urgent care billing team about your sites and payers.
Common questions
- How much do your urgent care billing services cost?
- Urgent care clinics pay 6.5% (1 clinician), 6.0% (2–5 clinicians) or 5.5% (6–15 clinicians) of insurance payments. Copays and self-pay fees carry 0%, and setup costs $0. See medical billing pricing for the minimum and the fee cap.
- Do we have to sign a long-term contract?
- No. Leave with 30 days' notice and no termination fee. Want a run-out? We keep working the claims we submitted for 90 days at your plan rate. Decline it and we charge nothing on payments that post after you leave. Notice by email; optional run-out covers claims we submitted before your exit date, at your plan rate; handover file within 10 business days of exit.
- How fast can you start billing for our urgent care centers?
- Go-live, when your first claims go out, comes within 5 business days of access; any unbilled backlog follows within 10 business days of access. Clock starts with your signed agreement, signed BAA and working system logins; it extends day for day while we wait on access. The six things we need from you are under how we start.
- Can you handle billing for several urgent care sites under one group?
- Yes. We set up each site with its own place of service, CLIA number and test list, bill every rendering clinician across all sites, and send the KPI report by the 10th of each month.
- Do you bill workers' compensation for work-injury visits?
- Yes. When the check-in answer says the injury happened at work, we bill the comp carrier first, not the patient's health plan, and follow that claim like any other open insurance balance.
- Which practice-management systems do you work in?
- We work inside your existing practice-management system and clearinghouse; tell us which ones and we confirm in writing within 1 business day. See EHR and practice-management compatibility.
- Can you credential new clinicians who join our urgent care?
- Yes. While you are a client, New-Clinician Enrollment covers new hires: Clinicians who join while you're a client get enrollment filed with up to 5 payers each (the payer decides), with no per-payer fee. Extra payers and new-site enrollments cost $149 per payer. Billed only after the payer confirms your effective date; $0 if denied or panel closed; filed within 5 business days of your complete packet.
Sources and review
Page revised October 7, 2026 · Review contact: Hyder Shah (inquiries@claimpillar.com). The workflow checklists are editorial recommendations; payer requirements depend on the program and current policy.
- CMS: Medicare Claims Processing Manual, Chapter 12 (POS rates, modifier 25, 99211 with injections, minor surgery)
- UnitedHealthcare: Urgent Care Policy, Professional (Commercial and Individual Exchange, 2026R0108A)
- Horizon BCBSNJ: Urgent Care Center Billing Requirements
- CMS: Transmittal 13465, CR 14273, New Waived Tests
- Novitas Solutions (JL): Modifier QW fact sheet
- CMS CY 2026 PFS relative value file (RVU26D)
- CMS: Medicare Secondary Payer (workers' compensation pays primary)