SLP CPT codes at a glance
The table is the SLP code sheet: evaluation, treatment, swallowing and AAC codes a speech practice meets on Medicare Part B claims. The labels are our own short descriptions, not the official CPT wording; the ASHA Medicare coding rules for SLP services list each code with its special Medicare rules. Amounts are the 2026 national Medicare amount (unadjusted, non-facility) from our dataset built on the CMS CY 2026 physician fee schedule relative value file; actual payment varies by locality, setting and payer.
The timed flag decides the units. ASHA notes that most codes SLPs report are untimed and bill once per day, regardless of the time spent. A timed code names its time in the descriptor, such as a first hour or each additional 30 minutes. The telehealth column reads the CMS list of Medicare telehealth services for CY 2026.
| Code | Our short label | Timed or untimed | On the 2026 Medicare telehealth list | 2026 national Medicare amount (unadjusted) |
|---|---|---|---|---|
| 92521 | Fluency evaluation | Untimed: 1 unit | Yes | $133.27 |
| 92522 | Speech sound production evaluation | Untimed: 1 unit | Yes | $111.89 |
| 92523 | Speech sound plus language evaluation | Untimed: 1 unit | Yes | $226.46 |
| 92524 | Voice and resonance evaluation | Untimed: 1 unit | Yes | $109.55 |
| 92507 | Individual speech-language treatment | Untimed: 1 unit | Yes | $76.15 |
| 92508 | Group speech-language treatment | Untimed: 1 unit | Yes | $24.05 |
| 92526 | Swallowing and feeding treatment | Untimed: 1 unit | Yes | $84.17 |
| 92610 | Clinical swallowing evaluation | Untimed: 1 unit | Yes | $84.84 ($57.78 facility) |
| 92611 | SLP part of a video swallow study | Untimed: 1 unit | No | $91.52 |
| 92605 | Non-speech-generating AAC evaluation, first hour | Timed | No | Bundled: no separate payment |
| 92618 | Add-on to 92605, each extra 30 minutes | Timed add-on | No | Bundled: no separate payment |
| 92606 | Non-speech-generating device therapy | Untimed: 1 unit | No | Bundled: no separate payment |
| 92607 | Speech-generating device evaluation, first hour | Timed | Yes | $122.25 |
| 92608 | Add-on to 92607, each extra 30 minutes | Timed add-on | Yes | $47.76 |
| 92609 | Speech-generating device therapy and programming | Untimed: 1 unit | Yes | $102.54 |
Evaluation codes 92521-92524
Four codes replaced the single speech evaluation code 92506, which ASHA records as deleted in 2014. Each one names the area the SLP evaluated, so the choice follows what the evaluation report actually covers. The guide below summarizes ASHA's notes on each code in our words.
How to choose the evaluation code
Start from the disorder areas the report documents, then check the pairing rule in the last column before the claim goes out.
One unit, however long the evaluation ran
The Medicare Claims Processing Manual, chapter 5, section 20.2 tells providers to enter 1 unit for a code not defined by a specific timeframe, and its example is a speech-language evaluation billed as 92521: regardless of the minutes spent, one unit is billed on the same day. The evaluation also starts the plan of care. Under the Medicare Benefit Policy Manual, chapter 15, a certification is timely when the physician or nonphysician practitioner dates it within 30 calendar days of the first treatment under that plan.
| If the evaluation covers | Bill | Pairing rule or note (ASHA) |
|---|---|---|
| Fluency, such as stuttering or cluttering | 92521 | One unit per day |
| Speech sound production only (articulation, phonology, apraxia, dysarthria) | 92522 | Not with 92523 |
| Speech sound production and receptive or expressive language | 92523 | Not with 92522 |
| Language only | 92523 with modifier 52 | 52 marks the reduced service |
| Voice and resonance, behavioral analysis | 92524 | Instrumental voice testing uses 31579, 92511 or 92520 |
| Auditory processing, by an SLP | 92523 | Treatment then bills under 92507 |
| Swallowing at bedside or in clinic | 92610 | See the swallowing section |
Treatment codes 92507 and 92508 (untimed)
92507 is individual speech-language treatment and 92508 is group treatment of two or more patients. Both are untimed, so a Medicare claim carries one unit per day for each, and a 30-minute and a 60-minute 92507 session bill the same. The Medicare Benefit Policy Manual, chapter 15, still expects the treatment note to record total treatment time in minutes, untimed minutes included. ASHA adds that SLPs use 92507 for aural rehabilitation and for training with voice prostheses.
Codes an SLP does not add to 92507
The 2026 NCCI Policy Manual, chapter 11 says SLPs shall not report 97110, 97112, 97150 or 97530 as unbundled services included in 92507, 92508 or 92526. It also bars a single practitioner from reporting 92507 or 92508 on the same date as cognitive codes 97129 and 97130 or sensory code 97533. When an SLP furnishes 92507 and an occupational therapist furnishes 97129 that day, an entity employing both may report both with an NCCI PTP-associated modifier. ASHA's coding FAQ notes that Medicare lets SLPs use 97129 and 97130 for cognitive treatment, but not with 92507 on the same day by the same provider.
2027: timed codes replace 92507
ASHA reports that 92507 remains in effect through December 31, 2026 and that ten timed codes take effect on January 1, 2027: a base code for the first 30 minutes and an add-on for each additional 15 minutes, in five clinical categories. 92508 becomes a stand-alone group code. CMS proposed Medicare values in the CY 2027 fee schedule proposed rule; the final rule sets them, and other payers decide if and when to adopt the codes. Do not report the new codes for 2026 dates of service.
| Treatment category from January 1, 2027 | Base code, first 30 minutes | Add-on, each extra 15 minutes |
|---|---|---|
| Fluency disorders | 92654 | 92655 |
| Speech sound production disorders | 92656 | 92657 |
| Language comprehension and expression disorders | 92658 | 92659 |
| Speech sound and language combined | 92660 | 92661 |
| Voice, upper airway or resonance disorders | 92662 | 92663 |
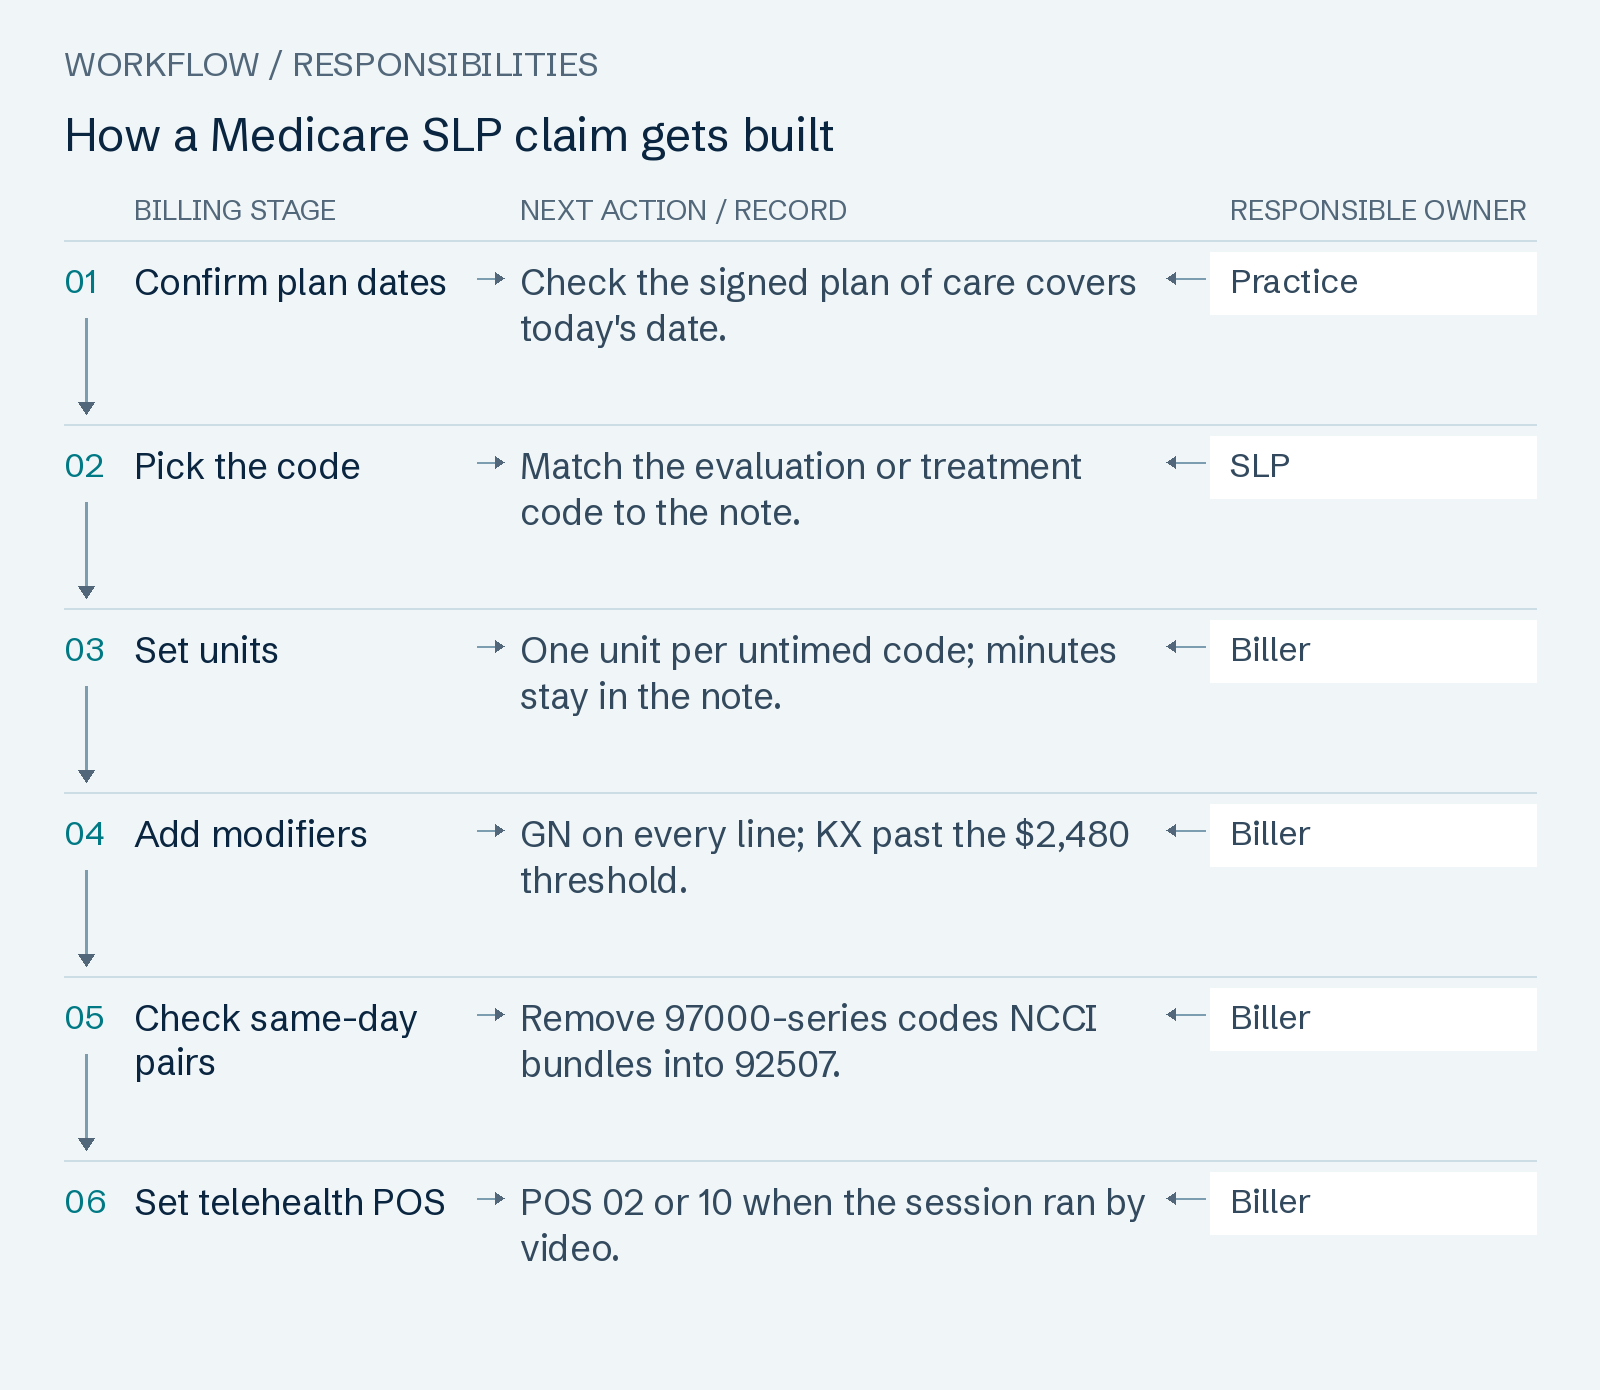
Read the workflow as text
- Confirm plan dates — Check the signed plan of care covers today's date. Owner: Practice.
- Pick the code — Match the evaluation or treatment code to the note. Owner: SLP.
- Set units — One unit per untimed code; minutes stay in the note. Owner: Biller.
- Add modifiers — GN on every line; KX past the $2,480 threshold. Owner: Biller.
- Check same-day pairs — Remove 97000-series codes NCCI bundles into 92507. Owner: Biller.
- Set telehealth POS — POS 02 or 10 when the session ran by video. Owner: Biller.
Swallowing and feeding: 92526, 92610, 92611
Dysphagia work splits into one treatment code and evaluation codes chosen by method. All bill one unit per day, and Medicare lines carry GN when the work sits under a speech-language pathology plan of care.
- 92526, swallowing and feeding treatment: the treatment session. NCCI chapter 11 says G0283, unattended electrical stimulation, shall not be reported with 92526 for stimulation used during the session, and the Medicare practitioner edit allows no modifier bypass. ASHA advises reporting 92526 rather than 97032 when electrical stimulation is part of a full swallowing session, and not reporting 92526 when the SLP performs only stimulation.
- 92610, clinical swallowing evaluation: the bedside or clinic evaluation. It is one of the few SLP codes with a separate facility amount: $84.84 non-facility and $57.78 facility (2026 national Medicare amount, unadjusted).
- 92611, the SLP's part of a videofluoroscopic swallow study: ASHA's FAQ says 92611 covers the SLP's participation in the modified barium swallow, while the radiologist reports 74230 separately. 92611 is not on the 2026 Medicare telehealth list.
Endoscopic studies use their own family: ASHA lists 92612 for FEES and 92616 when laryngeal sensory testing is added, with interpretation-only codes when the SLP does not pass the scope.
AAC device codes 92605-92609
Augmentative and alternative communication (AAC) codes split by device type. A speech-generating device produces digital or synthesized speech; a non-speech-generating device is a low-tech aid, per ASHA's coding FAQ.
Non-speech-generating devices: 92605, 92618, 92606
The CMS 2026 relative value file gives all three status B, bundled. ASHA states that Medicare won't pay for 92605 because it is considered bundled with any other speech-language pathology service on the same day, and that SLPs may not separately bill non-speech-generating device services alone. Commercial and Medicaid plans set their own policy.
Speech-generating devices: 92607, 92608, 92609
These pay under Medicare: $122.25 for 92607, $47.76 for the 92608 add-on and $102.54 for 92609 (2026 national Medicare amount, unadjusted). Bill a speech-generating device evaluation in this order:
- Report 92607 for the first hour of the evaluation.
- Add 92608 for each additional 30 minutes; ASHA says it is never billed apart from 92607.
- When the evaluation spans more than one day, submit the codes together using the last date of service, as ASHA advises.
- Report programming, modification and training with the device as 92609 at later visits.
GN modifier and Medicare rules
GN tells Medicare the service was delivered under an outpatient speech-language pathology plan of care; GO and GP name the occupational and physical therapy plans (chapter 5, section 20.1). Under section 10.4, contractors return claims for therapy codes from an SLP in private practice (specialty 15) that lack a therapy modifier, and ASHA's coding rules page applies GN to every code under a speech-language pathology or dysphagia plan.
The KX threshold speech shares with PT
The CMS therapy services page sets the 2026 KX threshold at $2,480 for PT and SLP services combined, with a separate $2,480 for OT, and says claims above it without KX are denied. A patient seeing both a PT and an SLP uses up one shared amount. The targeted medical review threshold is $3,000. The same page applies a 50 percent multiple procedure payment reduction to the practice expense of the second and later always-therapy services a patient receives on one day.
| Medicare rule | What it requires | Source |
|---|---|---|
| Discipline modifier | GN on every line under a speech plan of care | Claims Processing Manual ch. 5, §20.1 |
| Units | 1 unit per day for an untimed code | Ch. 5, §20.2 |
| Plan certification | Dated within 30 calendar days of the first treatment | Benefit Policy Manual ch. 15 |
| Recertification | During the plan or within 90 calendar days, whichever is less | Ch. 15 |
| Progress report | Covers no more than 10 treatment days | Ch. 15 |
| SLP assistants | Services denied as not reasonable and necessary | Ch. 15 |
| KX threshold | KX above $2,480 a year, PT and SLP combined | CMS therapy services page |
Telehealth SLP codes and modifiers
Speech-language pathologists can furnish Medicare telehealth through December 31, 2027. The CMS telehealth FAQ (updated October 8, 2026) says that starting January 1, 2028, SLPs, PTs, OTs and audiologists can no longer furnish Medicare telehealth services, and the CMS therapy services page ties the extension to section 6209 of the Consolidated Appropriations Act, 2026.
POS 02, POS 10 and modifier 95
On professional claims, the MLN telehealth booklet (MLN901705) uses POS 10 when the patient is at home and POS 02 when the patient is elsewhere. On institutional claims, it uses modifier 95 for outpatient therapy furnished by telehealth by SLPs employed by hospitals. GN stays on the line either way. Medicaid and commercial plans write their own telehealth rules, so check each payer's policy; our guide to telehealth billing for therapists sets out payer differences.
| SLP code group | On the CMS 2026 telehealth list | Codes |
|---|---|---|
| Evaluations | Yes | 92521, 92522, 92523, 92524 |
| Treatment | Yes | 92507, 92508 |
| Swallowing | Yes for 92526 and 92610; no for 92611 | 92526, 92610, 92611 |
| Speech-generating devices | Yes | 92607, 92608, 92609 |
| Non-speech-generating devices | No | 92605, 92606, 92618 |
| Cognitive treatment | Yes | 97129, 97130 |
Common SLP denials
Most SLP claim problems trace back to units, the discipline modifier, the plan of care or a same-day pair. Fix the cause before the claim goes out again.
If the same denials keep returning, the cause usually sits in the note template, the plan-of-care tracking or the charge setup, and the 2027 move to timed codes adds to it. Our speech therapy billing service bills SLP evaluations and treatment from the signed note to the posted payment, and a therapy billing company that also handles PT and OT can track the shared KX total across disciplines. OT evaluations and timed treatment codes are listed in the occupational therapy billing codes guide. Practices that add counseling bill time-based psychotherapy codes, explained in the 90837 CPT code guide.
To see where your open claims stand first, request The Free A/R Deadline Map: A claim-by-claim list of every unpaid insurance claim over 90 days in the aging report you send: payer, amount, the deadline it faces, the denial reason and the next action, sorted by deadline. Clock starts with your claim-level aging export and signed BAA; above 10 requests in a week, we confirm your date within 1 business day. Start the free A/R review.
| Problem | What happens | Fix |
|---|---|---|
| No GN on a private-practice SLP claim | Medicare returns the claim | Add GN and send a new claim |
| More than 1 unit of 92507 or an evaluation | Conflicts with the 1-unit rule for untimed codes | Correct to 1 unit; keep the minutes in the note |
| Over $2,480 without KX | Medicare denies the line | Add KX when the record supports medical necessity |
| 97530 or 97110 billed by the SLP | NCCI treats it as unbundled from 92507 | Remove the line; document the work under 92507 |
| 92507 with 97129 by one practitioner | NCCI same-day edit | Bill one; use the PTP modifier only when an SLP and an OT each furnished one |
| 92522 with 92523 | ASHA says not to bill them together | Bill 92523 alone when language was also evaluated |
| 92605 or 92606 to Medicare | Bundled: no separate payment | Check the payer's policy before billing other plans |
| Session by an SLP assistant | Medicare denies it as not reasonable and necessary | Bill only sessions the SLP furnished |
Common questions
- What is the CPT code for speech therapy treatment?
- 92507 for an individual session and 92508 for a group of two or more patients. Swallowing and feeding treatment uses 92526, and programming or training with a speech-generating device uses 92609. Under Medicare each is untimed, so one unit is billed per day, with GN on the line.
- Is 92507 a timed code?
- No. 92507 is untimed through December 31, 2026, so Medicare takes one unit per day whatever the session length (Claims Processing Manual, chapter 5, section 20.2). From January 1, 2027, ASHA reports that timed codes 92654 to 92663 replace it, each with a 30-minute base code and a 15-minute add-on.
- What are the speech evaluation codes?
- 92521 for fluency, 92522 for speech sound production, 92523 for speech sound production with language, and 92524 for voice and resonance. ASHA says not to bill 92522 with 92523, and to report a language-only evaluation as 92523 with modifier 52. Swallowing evaluations use 92610 or 92611; device evaluations use 92607 or 92605.
- Do SLP claims need the GN modifier?
- For Medicare, yes. GN shows the service was delivered under a speech-language pathology plan of care, and contractors return claims from SLPs in private practice that lack a therapy modifier. Medicaid and commercial plans set their own modifier rules, so check each payer's policy.
- Can a speech-language pathologist bill 97129 or 97530?
- 97129 and 97130 yes, for cognitive treatment, but not with 92507 or 92508 on the same day by the same practitioner, under NCCI chapter 11. 97530, 97110, 97112 and 97150 no: NCCI says SLPs shall not report them as unbundled services included in 92507, 92508 or 92526.
- Can speech therapy be billed as Medicare telehealth in 2026?
- Yes. 92507, 92508, the evaluations 92521 to 92524, 92526, 92610 and 92607 to 92609 are on the CMS 2026 telehealth list, and SLPs can furnish Medicare telehealth through December 31, 2027. Professional claims use POS 10 for a patient at home and POS 02 elsewhere.
Sources and review
Page revised November 5, 2026 · Review contact: Hyder Shah (inquiries@claimpillar.com). Every source below was retrieved and checked on November 5, 2026. Medicare amounts are 2026 national Medicare amounts (unadjusted) from our dataset built on the CMS CY 2026 PFS relative value file (RVU26D); actual payment varies by locality, setting and payer. Payer rules apply only to the payer named.
- CMS Medicare Claims Processing Manual, Chapter 5 (§10.4, §20.1, §20.2)
- CMS Medicare Benefit Policy Manual, Chapter 15 (plan certification, progress reports, SLP assistants)
- CMS: Therapy Services (2026 KX threshold, MPPR, SLP telehealth extension)
- CMS NCCI Policy Manual for Medicare Services 2026, Chapter 11
- CMS: List of Medicare Telehealth Services (CY 2026)
- CMS Telehealth FAQ (updated October 8, 2026)
- CMS MLN901705: Telehealth & Remote Monitoring (place of service and modifier 95)
- CMS CY 2026 PFS relative value files (RVU26D)
- ASHA: Medicare Coding Rules for Speech-Language Pathology Services
- ASHA: Coding FAQs for Speech-Language Pathologists
- ASHA: Speech-Language Pathology Treatment Codes Replacing 92507